GMP LPS
Lipopolysaccharide List™ HPT™ from Escherichia coli Type O113
9433 GMP LPS


9433 GMP LPS
For many years, List Biological Laboratories (List Labs) has manufactured various types of Lipopolysaccharides (LPS, a.k.a. endotoxin) as reagent grade material, that are for research use only. List Labs has also developed a purification method that is compliant with cGMP guidelines according to 21 CFR 211. The purification method yields a product that is sterilizable by filtration and free of protein and nucleic acids. This GMP compliant LPS drug product is available to clinical researchers with Investigational New Drug (IND) applications submitted to the Food and Drug Administration (FDA).
The bacterial strain used to produce GMP LPS is E. coli O113:H10:K-. This designates the O Antigen type (O113) of the Lipopolysaccharide (LPS), the flagella antigen type (H10) and capsule negative (K-). It is the type that was used for the National Reference Endotoxin1 and for the Second International Standard for Endotoxin.2 The intended use of these standards is as reference calibrants for bacterial endotoxin testing, such as pyrogenicity in rabbits or limulus amoebocyte lysate (LAL) assays. LPS type O113 has the structure typical of enteric bacteria and has the pro-inflammatory activity of a TLR-4 agonist.3
The cost of custom manufacturing of a GMP product is quite high when considering the small amount of LPS that is required for clinical trials. In addition, development costs for a custom product can not only be high, but also time consuming. Because List Labs has GMP LPS in stock, there is no time delay, and the cost is associated only with the needed amount of product and not the entire batch of material produced.
A Drug Master File has been submitted to FDA and has been accepted, also eliminating time delays due to regulatory issues.
List Labs GMP LPS, Catalog #9433A, is only available for purchase directly from List Labs.
The minimum order quantity for domestic purchases is 10 vials at 1μg (mcg) per vial.
The MOQ for international shipments is 25 vials at 1μg (mcg) per vial.
Please view and sign the required indemnification agreement (view and download)
List Labs requires 50% upfront payment to reserve and process your order, the balance is invoiced upon shipment. List Labs will arrange the temperature-controlled transportation. Shipping costs will be included in the final invoice. Purchaser is responsible for paying all customs duties and taxes.
Contact us for more information or to order GMP LPS
This product is appropriate for researchers doing clinical work under an IND which has been, or will be, submitted to FDA prior to use in humans. US customers can request an authorizing cross reference letter to the drug master file allowing them to cite the DMF, thereby allowing for FDA review. Currently, this product is being used by major pharmaceutical companies and universities, as well as the NIH Clinical Center for human studies.
Endotoxin has been used to study a variety of conditions that can be modeled by an inflammatory challenge with endotoxin/lipopolysaccharide from E. coli type O113. Suffredini, et al, reported the effects of intravenous endotoxin and discussed its role in the study of experimental inflammation.4 Bridging studies evaluated the effects of LPS manufactured by List Labs, administered intravenously, and concluded that a lot produced by List Labs is safe and produced the expected acute self-limiting inflammatory responses including pro-inflammatory cytokine responses with the expected level of adverse effects.5,6,7,8
Endotoxin is used as an inflammatory challenge to study treatment modalities for a variety of conditions that can be induced, such as depression,9,10,11,12 lung inflammation13,14 and cardio-metabolic disease.15,16 Fullerton describes the use of endotoxin by IV challenge to reproducibly model acute or chronic inflammation and to study the effects of therapeutic interventions.17
By the inhalation route, LPS induces inflammation and dendritic cell maturation as a Toll-like receptor 4 (TLR4) ligand.18 Ex vivo preparation of experimental cancer vaccines have utilized LPS in the cocktail to mature dendritic cells.19,20
This product is highly purified and well characterized. It is provided as a sterile lyophilized product in 1% lactose, 0.1% PEG6000, and is currently in stock.
A Certificate of Analysis is provided at shipment that includes a GMP compliance statement, certificate of origin and BSE/TSE statement.
GMP LPS is produced compliant to US FDA Good Manufacturing Practices guidelines found in 21 CFR 211. Please consult your internal Regulatory groups prior to use in humans.
List Labs is developing a cGMP production method for tetanus toxoid. Tetanus toxoid is a valuable hapten carrier in a population previously vaccinated with Tetanus-Diphtheria (TD) or Tetanus-Diphtheria-Acellular Pertussis (Tdap) vaccines. Contact us if you would like to receive more information when it becomes available.


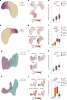
In vivo experimental human endotoxaemia model and ex vivo analyses
Eight healthy (as confirmed by medical history, physical examination and routine laboratory testing) male volunteers with ages ranging from 18 years to 35 years provided written informed consent to participate in experimental endotoxaemia experiments conducted at the research unit of the intensive care department of the Radboud University Medical Center. ...
A continuous endotoxin infusion regimen was used, as is described in detail elsewhere40. In short, participants were admitted to the research unit, and an antecubital vein and radial artery were cannulated to allow administration of fluids and endotoxin, and blood sampling and haemodynamic monitoring, respectively. A 3-lead ECG was recorded continuously throughout the experiment. After iso-osmolar pre-hydration (1.5 l NaCl 0.45% and glucose 2.5% administered intravenously in the hour before the start of endotoxin infusion), volunteers were intravenously challenged with a loading dose of 1 ng kg−1 bodyweight endotoxin (Escherichia coli lipopolysaccharide (LPS) type O113, lot no. 94332B1; List Biological Laboratories), directly followed by continuous infusion of 0.5 ng kg−1 h−1 for 3 h. Participants were monitored for 8 h after the endotoxin loading dose after which they were discharged from the research unit. ...
Experimental human endotoxemia
All endotoxemia-related procedures were performed according to our standard continuous LPS-infusion protocol (12). In short, subjects were admitted to the research unit situated on the Medium Care department of the Radboud university medical center for approximately ten hours. Subjects had to refrain from consumption of alcohol and caffeine (24 h), and food and drinks (12 h) prior to LPS administration. Upon admission on the first LPS challenge day, two antebrachial venous cannulas were placed to allow administration of fluids, study medication and LPS. A radial artery catheter (BD Infusion Therapy Systems, Sandy, Utah, USA) was placed under ultrasound guidance to allow serial blood sampling and continuous hemodynamic monitoring. To reduce the risk of vasovagal responses (14), hydration fluids (2.5% glucose/0.45% sodium chloride) were administered as an initial prehydration bolus of 1.5L in the 45 min prior to LPS administration, and at a rate of 150 mL/hr for the remainder of the experiment. After prehydration, a bodyweight adjusted bolus dose of 1 ng/kg LPS (E. coli type O:113, lot no. 94332B1; List Biological Laboratories, Campbell, USA) was administered intravenously, directly followed by continuous infusion of LPS at a rate of 0.5 ng/kg/hr for three hours. Blood samples were serially obtained to construct time-concentration curves of circulating cytokines. Heart rate and intra-arterial blood pressure were measured using a 4-lead electrocardiogram (M50 Monitor, Philips, Eindhoven, the Netherlands) and a radial artery pressure transducer (Edwards Lifesciences, Irvine, California, USA). Hemodynamic parameters were recorded every 5 s using in-house developed software. Every 30 min, body temperature was measured using a tympanic thermometer (FirstTemp Genius 2, Covidien, Dublin, Ireland). Flu-like symptoms (headache, nausea, cold shivers, myalgia and back pain) were scored every 30 min using a numeric six-point Likert scale (0 = no symptoms, 5 = worst ever experienced). A composite score was then calculated as the sum of all previous elements, resulting in a total symptom score ranging from 0 to 25. Furthermore, general malaise was scored on an eleven-point scale (0 = no symptoms, 10 = worst ever experienced).
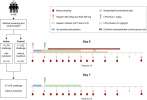


2.2. General session procedures
We performed all LPS-related procedures as described previously (Jansen et al., 2022). We tested three participants simultaneously in one room at the Medium Care Unit of Radboudumc. Sixty to 90 min before LPS administration, we placed a radial artery catheter and antebrachial venous cannula to allow serial blood sampling, hemodynamic monitoring, and administration of fluids and LPS, respectively and these stayed in during the remaining of the test-day. In the 45 min prior to LPS administration, we administered hydration fluids (2.5% glucose / 0.45% sodium chloride) as a 1.5L prehydration bolus to reduce the risk of vasovagal collapse(van Eijk et al., 2004), and thereafter at a rate of 150 mL/h for the remainder of the experiment. Directly after prehydration, we administered a bodyweight-adjusted bolus dose of 1 ng/kg LPS (E. Coli-derived, Type O113, lot no. 94332B1; List Biological Laboratories) intravenously. Behavioural testing took place at three timepoints: 45 min before injection (S1), 2 h post injection (S2) and 5 h post injection (S3). Timing was based on previous studies showing that sickness symptoms and cytokines peak 1.5-2 h after LPS administration and are largely normalized 5 post-LPS administration (Kox et al., 2015, Leentjens et al., 2012). At S2, participants were able to perform behavioural tasks while cytokine levels and fatigue are still high (Draper et al., 2018). Participants filled out mood questionnaires each hour after LPS administration. Furthermore, we obtained blood samples at various timepoints prior to and following LPS administration (see below). ...
2.3. Experimental human endotoxemia
Subjects were admitted twice to the intensive care research unit of the Radboud university medical center in Nijmegen, The Netherlands, to receive both LPS challenges. All subjects underwent the same procedures on both hospitalization days which were 7 days apart. One day prior to both admissions, subjects needed to refrain from alcohol and caffeine, and no food or drinks were allowed from 10 hours before start of the challenge days. After admission, an intravenous cannula was inserted in the antebrachial vein to administrate fluids and LPS. A radial artery catheter was placed to withdraw blood and monitor blood pressure continuously. One hour before the challenge, 1.5 L prehydration fluid (2.5% Glucose/0.45% NaCl) was administered. Subsequently, a bolus of 2 ng/kg LPS (E. coli type O113, Lot no. 94332B1; List Biological Laboratories, Campbell, USA) was administered intravenously and similar hydration fluid was continued at an infusion rate of 150 mL/h for 8 hours. Heart rate was monitored using a 4-lead electrocardiogram (M50 Monitor, Philips, Eindhoven, The Netherlands) and intra-arterial blood pressure was measured with a pressure transducer (Edward Lifesciences, Irvine, USA). Every 30 minutes, we measured core temperature with a tympanic thermometer (FirstTemp Genius 2, Covidien, Dublin, Ireland) and LPS-induced symptoms (headache, nausea, cold shivers, muscle- and back pain) were scored using a numeric six-point scale (0 = no symptoms, 5 = worst symptoms experienced ever). The sum of these scores in addition of 3 points in case of vomiting, resulted in a total symptom score ranging from 0 to 28. Blood was withdrawn before prehydration (T = -60 minutes), just before LPS administration (T = 0 minutes), and respectively 60, 90, 120, 180, 240, 360 and 480 minutes after the LPS bolus. Plasma cytokine concentrations (tumour necrosis factor-alpha (TNF-α), interleukin (IL)-6, IL-8, IL-10, macrophage inflammatory protein (MIP)-1α, MIP-1β, monocyte chemoattractant protein (MCP)-1 and IL-1RA (receptor antagonist)) were determined batchwise using a simultaneous luminex assay (Milliplex, Millipore, Billerica, USA).
... Intravenous LPS challenge. Intravenous LPS challenges were only performed on occasion 2 and 3. Subjects received 1 ng/kg (cohort 1) or 2 ng/kg (cohort 2) E. Coli-purified LPS (GMP-grade from Lot#94332B4, List Biological Laboratories Inc ...
Experimental Human Endotoxemia (IV LPS Administration)
All experimental endotoxemia-related procedures were performed as described previously and were identical on both LPS challenge days (days 0 and 7) [19, 22]. In short, subjects were admitted to the research unit of the Radboud University Medical Center for 8 h. Subjects had to refrain from alcohol and caffeine (24 h) and food and drinks (12 h) prior to LPS administration. A radial artery catheter (BD Infusion Therapy Systems, Sandy, UT, USA) and antebrachial venous cannula were placed to allow serial blood sampling, hemodynamic monitoring, and administration of fluids and LPS, respectively. In the 45 min prior to LPS administration, hydration fluids (2.5% glucose/0.45% sodium chloride) were administered as a 1.5-L prehydration bolus to reduce the risk of vasovagal collapse [23] and thereafter at a rate of 150 mL/h for the remainder of the experiment. Directly after prehydration, a bodyweight-adjusted bolus dose of 1 ng/kg LPS (Escherichia coli-derived, Type O113, lot No. 94332B1; List Biological Laboratories, Campbell, CA, USA) was administered. Blood samples were serially obtained to construct time-concentration curves of circulating cytokines.
2.5. Experimental human endotoxemia
On days 0 and 7, experimental endotoxemia was performed according to our standardized protocol8. Briefly, subjects were admitted to the research unit of the Radboud university medical center for eight hours, where a radial artery catheter (BD Infusion Therapy Systems) and antebrachial venous cannula were placed to allow serial blood sampling, hemodynamic monitoring and administration of fluids and LPS, respectively. In the 45 minutes prior to LPS administration, hydration fluids (2.5% glucose/0.45% sodium chloride) were administered as a 1.5L prehydration bolus to reduce the risk of vasovagal collapse13, and thereafter at a rate of 150 mL/h for the remainder of the experiment. Directly after prehydration, a bodyweight-adjusted bolus dose of 1 ng/kg LPS (E. Coli-derived, Type O113, lot no. 94332B1; List Biological Laboratories) was administered.
Human blood samples
For volunteers treated with endotoxin, blood samples were acquired from a random 17 out of 100 volunteers who participated in the 100LPS human endotoxemia study (NL68166.091.18, CMO: 2018-4983). ...
On the day of the LPS challenge, volunteers were hospitalized at the Radboud University Medical Center and received a single intravenous administration of 1 ng/kg LPS (Escherichia coli O:113; List Biological Laboratories, Campbell, CA, USA), inducing controlled systemic inflammation. Participants were constantly monitored by a care physician for sepsis-related symptoms such as high blood pressure, high heart rate or fever, among others. ...
Systemic LPS challenge
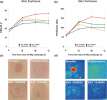
After participants had undergone the IMQ skin challenge, an i.v. LPS challenge was performed on Day 7 after the start of treatment. All participants received 1 ng/kg purified Escherichia coli O113 LPS (List Labs, US, Lot #94332B4) reconstituted in 0.5 mL glucose 2.5%-sodium chloride (NaCl) 0.45% and administered as a 2- min infusion. To ensure that participants stayed adequately hydrated, glucose 2.5%-NaCl 0.45% was infused, starting 2 h prior to LPS administration and continuing until 6 h afterwards.18 Circulating inflammatory proteins (acute phase proteins, cytokines), leukocyte differentiation, and clinical parameters (pulse rate, blood pressure, and temperature) were evaluated over time, starting 0.5 h after the end of the infusion and ending up to 24 h after infusion.

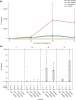
- One hour prior to study drug administration, systemic inflammation was induced by bolus administration of 1 ng/kg Escherichia coli type O113 lipopolysaccharide (LPS; List Biological Laboratories Inc. Campbell, California, USA) ...


List Biotherapeutics
9800 Crosspoint BIvd Suite 2011
Indianapolis, IN 46256, USA



 Find a distributor near you